Respiratory syncytial virus, or RSV, is often discussed as an infection of babies. It also matters at the other end of life. In older adults, particularly those with heart or lung disease, immunocompromise or frailty, RSV can cause lower-respiratory disease and hospitalisation.
That makes Australia’s latest immunisation change important. From May 2026, the National Immunisation Program funds a single dose of the RSV vaccine Arexvy for all adults aged 75 years and over, and for Aboriginal and Torres Strait Islander adults aged 60 years and over. The Australian Immunisation Handbook also recommends vaccination from age 60 when medical risk factors for severe RSV disease are present.
This is a genuine preventive advance. It is not, however, a reason to treat every person over 60 as having the same risk or to describe vaccination as a guarantee. The useful question is how the mechanism, trial evidence, real-world data and remaining uncertainties fit together.
Why age changes the RSV conversation
RSV can infect people repeatedly because natural infection does not create reliably lasting immunity. For many adults it causes an upper-respiratory illness. The chance of serious lower-respiratory disease rises with age and with conditions that reduce respiratory, cardiac or immune reserve.
Ageing also changes the immune response. The antibody and T-cell systems do not simply switch off, but their coordination, diversity and response to a new antigen can become less efficient. That is one reason some vaccines for older adults use an adjuvant: an additional component designed to strengthen the immune signal generated by the vaccine antigen.
These are mechanistic principles. They explain why vaccine design and baseline risk matter; they do not tell us the size of benefit for an individual.
A structural biology problem unlocked the vaccine
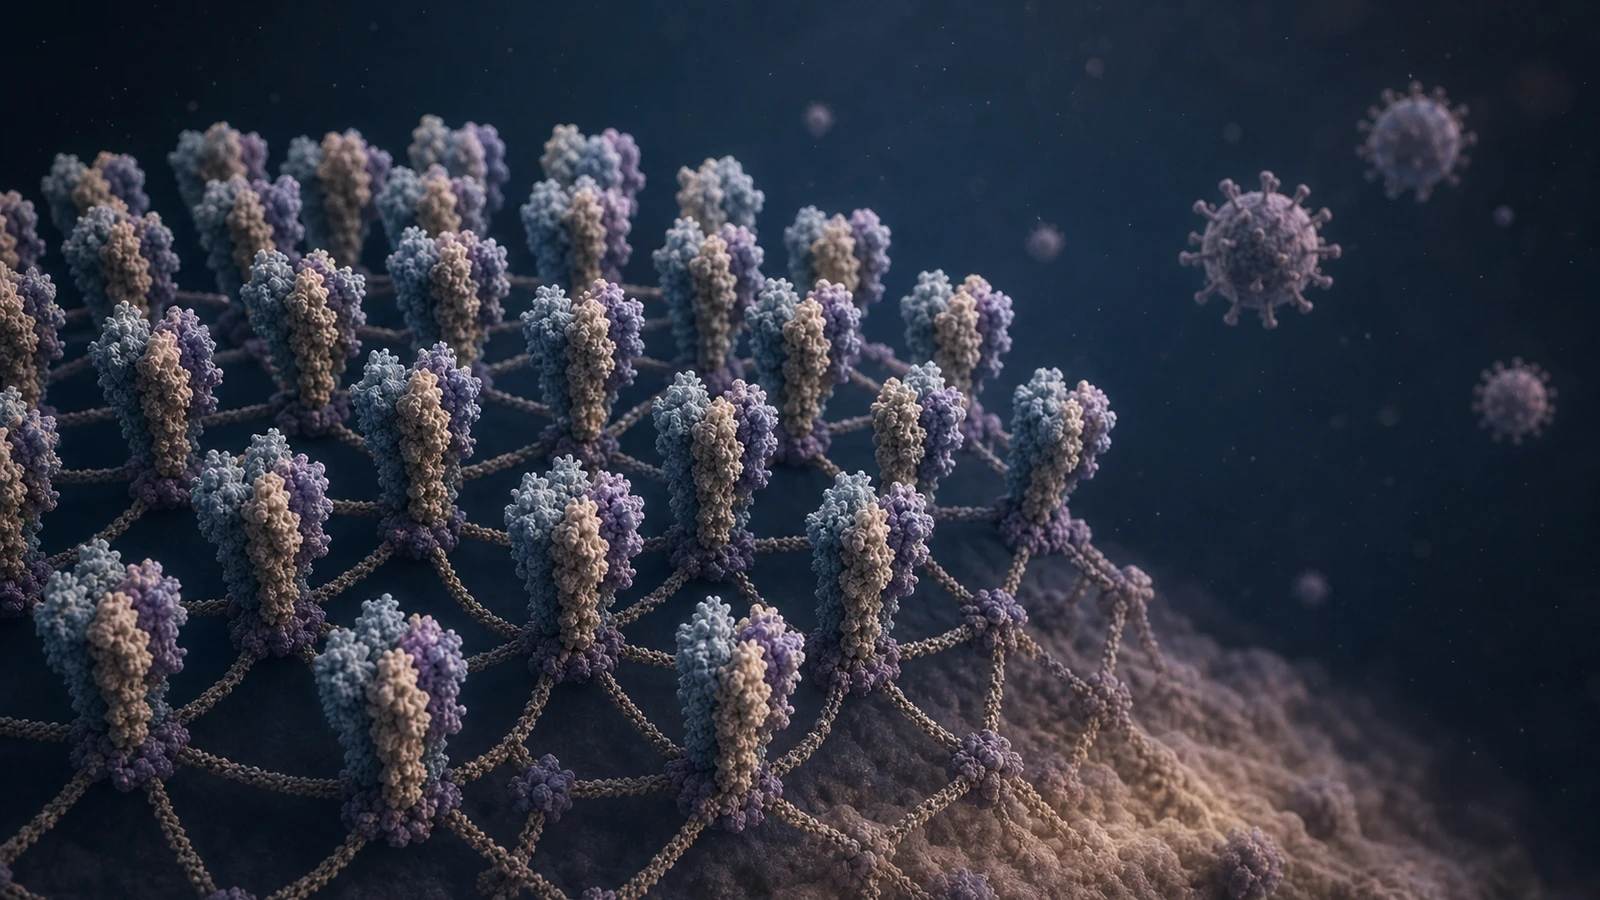
RSV enters cells using a fusion protein called F. Before fusion, that protein sits in an unstable prefusion shape. It then rearranges into a different postfusion form. Some of the most potent neutralising antibodies recognise sites that are best exposed in the prefusion shape.
In 2013, NIH researchers reported structure-guided methods for stabilising the F protein in that prefusion state. This was a molecular and preclinical breakthrough: it produced an antigen that generated strong neutralising responses in animal models and provided a platform for later human vaccines.
Australia’s two registered older-adult RSV vaccines both present prefusion F protein. Arexvy uses one prefusion-F antigen with an adjuvant; Abrysvo uses prefusion-F antigens from RSV A and B without an adjuvant. Understanding that design is useful, but immune-response measurements are still surrogate outcomes. Clinical trials were needed to learn whether vaccinated people developed less RSV disease.
What the human trial found
The pivotal Arexvy trial randomly assigned nearly 25,000 adults aged 60 years or over to vaccine or placebo before an RSV season. During the first season, vaccine efficacy against confirmed RSV lower-respiratory tract disease was about 83 per cent. Protection extended into later seasons, but the estimated efficacy was lower when the second and third seasons were examined separately.
Relative efficacy needs context. RSV lower-respiratory disease was uncommon in both trial groups, so the absolute number of cases avoided depends heavily on a person’s starting risk. An adult aged over 75 with chronic heart or lung disease may have more to gain than a healthy person in their early 60s. This is consistent with Australia’s age- and risk-based recommendations.
Post-licensure studies now add evidence from routine care. A 2026 systematic review and meta-analysis found that older-adult RSV vaccination was associated with fewer RSV-related hospitalisations and emergency-department visits. These data cover much larger and more varied populations than the original trials, but they are observational. Differences in who seeks vaccination, testing practices, seasons and health systems can affect the estimates.
Effectiveness and safety are both continuing questions
Common reactions to Arexvy in the clinical trials included injection-site pain, fatigue, muscle aches and headache. Serious adverse-event rates were similar between vaccine and placebo groups. Trials of this size cannot reliably detect every very rare event, which is why post-market surveillance matters.
Australian guidance now notes a very small excess of Guillain–Barré syndrome reports after older-adult RSV vaccination: early overseas surveillance estimated about 5–7 excess cases per million Arexvy doses and 9–18 per million Abrysvo doses within 42 days, against an expected background rate of about two per million. These estimates remain under review. A previous history of Guillain–Barré syndrome is therefore a specific reason to discuss individual risks and benefits with a clinician.
The duration question is also unfinished. Current Australian guidance describes protection for at least two years and recommends a single dose. The need for later doses has not yet been established, so RSV vaccination should not be assumed to follow the annual influenza schedule.
What the Australian program means in practice
The current categories are deliberately not identical:
- adults aged 75 years and over are recommended to receive one dose, with Arexvy funded nationally;
- Aboriginal and Torres Strait Islander adults aged 60 years and over are recommended to receive one dose, with Arexvy funded nationally;
- adults aged 60 years and over with medical risk factors for severe RSV disease are recommended to receive one dose, although funding can depend on eligibility and jurisdiction; and
- non-Indigenous adults aged 60–74 years without a listed risk factor may consider vaccination, recognising that their expected absolute benefit is generally smaller.
Vaccination can be given at any time, although the Handbook prefers administration before the usual RSV season where practical. A calm discussion can cover age, medical risks, previous vaccine reactions, prior Guillain–Barré syndrome, likely benefit, access and the fact that recommendations may evolve as longer-term data accumulate.
The broader healthy-ageing lesson is not that every new preventive tool belongs in every plan. It is that a sound program links a well-defined risk group to a studied intervention, tracks uncommon harms and updates the interval as evidence matures.
Sources
- Australian Immunisation Handbook: respiratory syncytial virus recommendations and evidence (updated May 2026)
- Science: structure-based design of a prefusion RSV F vaccine antigen (2013)
- New England Journal of Medicine: phase 3 RSVPreF3 OA trial in older adults (2023)
- The Lancet Regional Health – Europe: real-world systematic review and meta-analysis (2026)
Evidence note: This Insight is general education, not medical advice. It does not determine personal vaccine eligibility or replace an individual discussion with a qualified clinician or immunisation provider using current Australian guidance.